
Epidural and Spinal Procedures on Anticoagulants: Managing Hematoma Risks
 Sep, 1 2026
Spinal Procedure Risk Estimator
This tool helps patients and providers visualize the relative risk of Spinal Epidural Hematoma (SEH) based on current medication status and procedural factors. It is an educational aid and does not replace clinical judgment.
Patient & Medication Factors
Select options and click Calculate to see your estimated risk level.
Note: "Low" does not mean zero risk. Always follow ASRA guidelines for hold times.
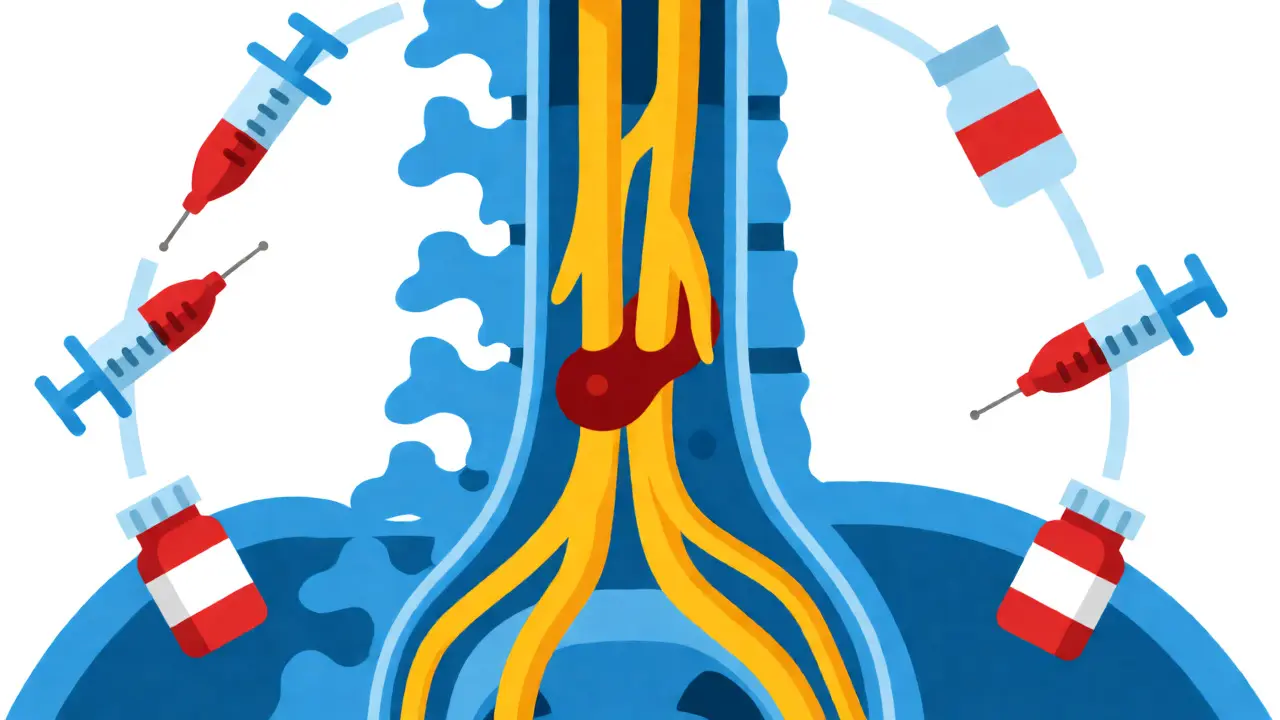
Imagine waking up from a routine back procedure unable to move your legs. It sounds like a nightmare, but for patients on blood thinners undergoing spinal or epidural procedures, this is a real, albeit rare, medical emergency known as Spinal Epidural Hematoma (SEH). While the incidence is low-roughly 1 in 150,000 standard epidural blocks-the consequences are devastating. A tiny amount of blood, just 1-2 mL, can compress the spinal cord within the confined space of the spinal canal, leading to permanent paralysis if not treated immediately.
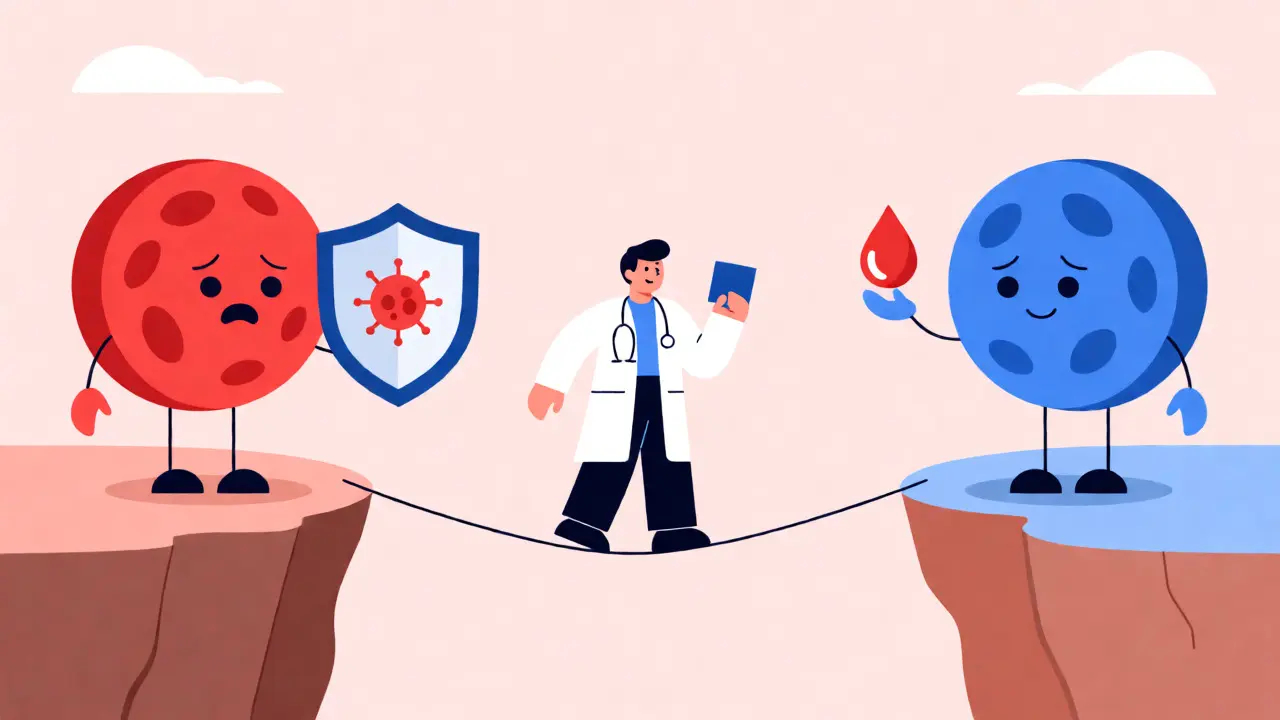
The core challenge here isn't just the procedure itself; it's the delicate balance between preventing clots and preventing bleeding. Stop the blood thinners too long, and you risk a life-threatening stroke or pulmonary embolism. Keep them going too close to the needle stick, and you risk a hematoma that could leave you paraplegic. This article breaks down exactly how clinicians navigate this high-stakes tightrope walk using current evidence-based protocols.
Understanding the Risk: Why Blood Thinners Matter
Anticoagulant therapy disrupts the body’s natural clotting cascade. When you introduce a needle into the epidural or subarachnoid space, you create a potential site for bleeding. Normally, your body plugs that hole quickly. But under the influence of drugs like warfarin or heparin, that plug forms slowly or not at all. The result? Blood pools around the spinal nerves.
It’s not just about the drug type; timing is everything. The American Society of Regional Anesthesia and Pain Medicine (ASRA) has spent years refining guidelines to minimize these risks. Their data shows that the risk of SEH is directly proportional to the intensity of anticoagulation. For instance, therapeutic doses of Low Molecular Weight Heparin (LMWH) carry a significantly higher risk than prophylactic doses. If you’re on a "blood thinner," your provider needs to know exactly what you’re taking, when you took it last, and why you’re taking it.
Clinical Warning Signs: Catching It Early
Time is muscle-or in this case, nerve function. The critical window for intervention is within 8 hours of symptom onset. Studies show that 79% of patients who receive surgical decompression within this window achieve full neurological recovery. Wait longer than 24 hours, and that success rate plummets to 9%. So, what should you look for?
- Midline Back Pain: Reported in 93% of cases. This isn’t just soreness from the injection; it’s often severe and persistent.
- Sensory Deficits: Numbness or tingling in the legs or groin area (saddle anesthesia).
- Motor Weakness: Difficulty moving legs or feet, such as foot drop.
- Bowel/Bladder Dysfunction: Inability to urinate or loss of bowel control.
If any of these symptoms appear after a spinal procedure, it’s an emergency. Don’t wait for your next scheduled appointment. Immediate MRI imaging and neurosurgical consultation are required to rule out a hematoma.
Risk Stratification: Who Is Most Vulnerable?
Not everyone faces the same level of danger. Certain factors dramatically increase the likelihood of complications. Understanding these helps tailor the approach for each patient.
| Risk Factor Category | Specific Condition | Impact on Risk |
|---|---|---|
| Medication Status | INR > 1.4 (Warfarin) | 8.7-fold increased risk |
| Medication Status | Therapeutic LMWH within 8 hours | Relative Risk 4.3 |
| Procedural Technique | Traumatic Puncture (bloody tap) | 11.8-fold increased risk |
| Patient History | Age > 70 years | Odds Ratio 3.7 |
| Patient History | Renal Impairment (CrCl < 30) | Odds Ratio 4.9 |
Notice how technical skill plays a huge role. A "traumatic puncture"-where the needle hits a vessel and causes bleeding during insertion-is one of the strongest predictors of hematoma formation. This highlights why choosing an experienced provider matters just as much as managing your medications.
Managing Specific Anticoagulants: Timing is Everything
Different drugs require different "washout" periods before a spinal procedure. You cannot treat every blood thinner the same way. Here is how the major classes are handled according to recent ASRA guidelines:
Warfarin (Coumadin)
For patients on warfarin, the International Normalized Ratio (INR) must be checked within 24 hours of the procedure. The target is typically an INR below 1.4. If the INR is higher, the procedure might need to be postponed. After the procedure, warfarin can usually be resumed 4 hours later for single injections, or 6 hours later if an epidural catheter was placed.
Low Molecular Weight Heparin (LMWH)
LMWH, such as enoxaparin (Lovenox), requires strict timing. Prophylactic doses should be held for 10-12 hours before the procedure. Therapeutic doses require a longer break-24 hours. Resumption is delayed by at least 2 hours post-procedure for single shots, or 4 hours for catheters. The FDA has highlighted specific risks with Lovenox, noting over 100 confirmed cases of spinal hematomas linked to its use.
Direct Oral Anticoagulants (DOACs)
Drugs like rivaroxaban (Xarelto) and apixaban (Eliquis) have predictable half-lives but depend heavily on kidney function. For normal renal function, a 48-hour cessation period is recommended. If you have impaired kidneys, this extends to 72 hours. These drugs don’t have simple blood tests to monitor their effect instantly, making strict adherence to timing crucial.

The Antiplatelet Debate: Aspirin vs. Clopidogrel
This is where experts disagree. Should you stop aspirin? Many pain specialists argue no. A study of 1,204 procedures found zero hematomas when aspirin was continued. However, dual antiplatelet therapy (taking aspirin plus clopidogrel or ticagrelor) is different. Combining these agents increases the risk nearly fourfold. Most guidelines suggest holding clopidogrel for 5-7 days before invasive spinal procedures, while continuing aspirin alone is often considered safe.
Practical Steps for Patients and Providers
How do you ensure safety in the real world? It comes down to communication and documentation.
- Full Medication List: Bring every pill bottle to your pre-op visit. Include supplements like fish oil or ginkgo biloba, which can also affect bleeding.
- Confirm Timing: Ask explicitly: "When did I take my last dose?" Write it down. Errors in timing account for a significant portion of adverse events.
- Monitor Symptoms: After the procedure, stay alert for the warning signs listed above. If you feel numbness or weakness, call your provider immediately.
- Use Decision Tools: Apps like "Neuraxial Anticoag" help providers calculate hold times accurately, reducing human error.
Despite rigorous protocols, near-misses happen. A survey of pain physicians revealed that only 58% correctly identified all timing requirements without assistance. This underscores the value of using standardized checklists rather than relying solely on memory.
Can I have an epidural if I am on blood thinners?
Yes, but only if the medication is managed correctly. You will likely need to pause your anticoagulant for a specific number of hours or days before the procedure, depending on the drug type and your kidney function. Your doctor will weigh the risk of bleeding against the risk of forming a clot.
What happens if I develop a spinal hematoma?
This is a medical emergency requiring immediate diagnosis via MRI and urgent surgical decompression (laminectomy). Success depends heavily on speed; surgery within 8 hours offers the best chance of full recovery. Delayed treatment often results in permanent neurological deficits.
Is aspirin safer than other blood thinners for spinal injections?
Generally, yes. Continuing aspirin monotherapy is associated with a very low risk of spinal hematoma (approximately 0.03%). However, combining aspirin with another antiplatelet agent like clopidogrel significantly raises the risk and usually requires stopping one or both agents before the procedure.
Why do older adults have higher risks?
Advanced age (>70 years) is an independent risk factor due to physiological changes in blood vessels and slower clearance of medications. Additionally, older patients are more likely to have comorbidities like renal impairment, which further prolongs the effect of anticoagulants.
What is the difference between prophylactic and therapeutic dosing?
Prophylactic doses are lower amounts used to prevent clots from forming (e.g., after surgery). Therapeutic doses are higher amounts used to treat existing clots (e.g., deep vein thrombosis). Therapeutic doses carry a significantly higher bleeding risk and require longer hold times before spinal procedures.
Eryn Manchego
September 3, 2026 AT 10:02the risk stratification table is honestly the most useful part of this whole thing. i always get so anxious about the timing windows but seeing the odds ratios laid out like that makes it feel way more manageable. its wild how much a bloody tap changes the game though, 11.8 fold increase is no joke. we need to talk more about provider skill because meds are only half the battle.
Crystal Torres
September 3, 2026 AT 11:58The distinction between prophylactic and therapeutic dosing for LMWH is critical and often overlooked in patient education materials. It is imperative that patients understand why their hold times differ based on the indication for therapy rather than just the drug name alone. Clear communication regarding these specific timeframes can significantly reduce pre-procedure anxiety and improve compliance with safety protocols.
Patrick van der Velde
September 4, 2026 AT 10:24It is frankly amusing that we still have to explain basic pharmacokinetics to practitioners who claim expertise in regional anesthesia. The reliance on ASRA guidelines is necessary precisely because too many clinicians treat anticoagulation management as an afterthought rather than a core competency. If you cannot calculate a simple washout period without checking an app every single time perhaps you should reconsider your specialty choice entirely. This isn't rocket science it's basic physiology applied to clinical practice yet we see errors persisting year after year due to sheer laziness or lack of attention to detail.
Pearl Richardson
September 5, 2026 AT 21:03They hide the real stats from us 🤨 the 1 in 150,000 figure is manipulated by industry shills who want to sell you needles. Real world data shows higher rates especially when they use those cheap traumatic needles on elderly patients with bad kidneys 📉. Why do they never mention the pharmaceutical kickbacks? It’s all about profit over paralysis 🏥💸.
larry williams
September 7, 2026 AT 01:36I appreciate the thorough breakdown of the warning signs here because early detection really is the key to preserving function. It is important to remember that while the statistics are reassuringly low the emotional toll on patients waiting for those results can be immense. We must support our colleagues in maintaining vigilance during the post-procedure monitoring phase since complacency is often the enemy of safety. Every team member has a role to play in ensuring that if symptoms arise they are addressed with urgency and precision.
Stephen Horn
September 8, 2026 AT 07:30The assertion that aspirin monotherapy is safe ignores the subtle vascular fragility present in many comorbid patients. One must consider the systemic inflammatory state which exacerbates bleeding risks regardless of platelet inhibition levels. Furthermore the anecdotal evidence provided regarding zero hematomas lacks the rigor of large scale multicenter trials. Until proven otherwise I maintain that caution is the hallmark of superior medical judgment.
Gurjit Singh
September 10, 2026 AT 01:40We must acknowledge the ethical responsibility physicians bear when balancing thrombotic versus hemorrhagic risks. It is not merely a technical decision but a moral one affecting quality of life. Patients deserve full transparency about these tradeoffs so they can participate meaningfully in shared decision making processes.
kishhore kumar
September 10, 2026 AT 11:29this is super helpful info! i had my back procedure last month and was terrified about stopping my meds. glad to see there are clear rules now. hope everyone stays safe out there 💪🙌